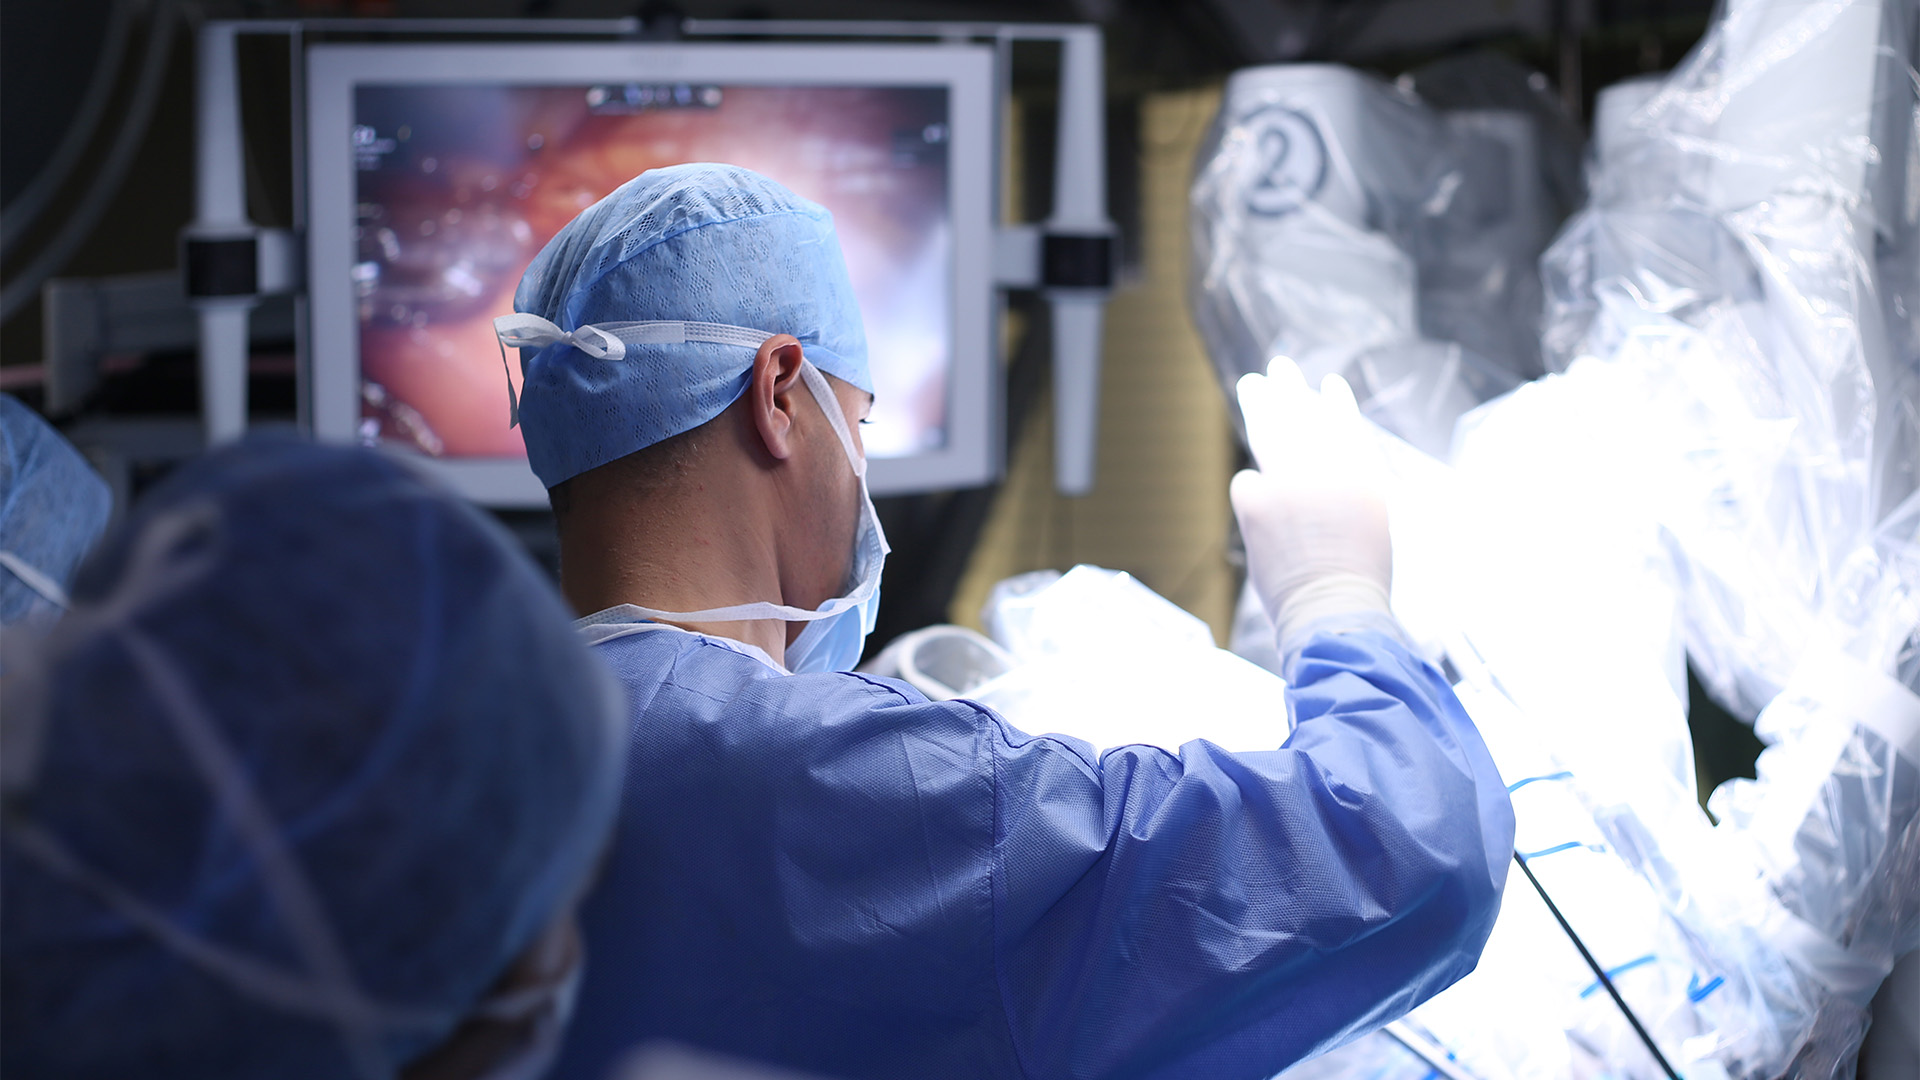
This video presents the authors’ standardized technique for multiportal robotic-assisted left pneumonectomy after neoadjuvant chemoimmunotherapy, using a five-step hilar dissection based on the principles of the French lobectomy approach.
In this setting, treatment-related inflammatory and fibrotic changes may make hilar dissection particularly challenging. The robotic platform provides enhanced three-dimensional visualization, wristed instrumentation, and precise dissection, which may facilitate vascular and bronchial control in these complex post-induction cases.
The patient was positioned in the right lateral decubitus position under general anesthesia with single-lung ventilation using a double-lumen endotracheal tube. A four-arm robotic approach was used, with ports positioned in a W-shaped configuration. The camera port was placed in the sixth intercostal space, and the anterior utility port was positioned sufficiently low to facilitate bronchial stapling.
The procedure began with division of the inferior pulmonary ligament, which allowed for the mobilization of the lower lobe and exposure of the inferior pulmonary vein. Station 9 lymph nodes were removed, and the inferior pulmonary vein was circumferentially dissected and divided using a vascular stapler.
The second step consisted of posterior hilar dissection. The posterior mediastinal pleura was opened, which provided access to the subcarinal space. Stations 7 and 10 lymph nodes were systematically dissected. This posterior approach progressively exposed the left main bronchus and contributed to circumferential hilar mobilization.
The third step involved opening the superior mediastinal pleura. Station 5 lymph nodes were removed, and the proximal pulmonary artery was progressively exposed. Particular attention is required after chemoimmunotherapy because inflammatory adhesions and fibrosis may obscure the usual tissue planes. The magnified robotic view and articulated instruments allowed for meticulous dissection while maintaining direct visualization of the vascular structures.
The fourth step consisted of anterior hilar dissection. The superior pulmonary vein was circumferentially isolated and divided with a vascular stapler. The pulmonary artery was then completely dissected and divided under direct robotic visualization. Sequential vascular control progressively mobilized the lung and improved exposure of the main bronchus.
During the fifth and final hilar step, the left main bronchus was circumferentially dissected and divided close to the carina, keeping the bronchial stump as short as safely possible. An underwater air-leak test was performed to confirm bronchial stump integrity.
After completion of the pneumonectomy and systematic lymph node dissection, the specimen was placed in a retrieval bag. A wound retractor was inserted, and a limited thoracotomy incision was performed to allow for the controlled extraction of the specimen.
At the end of the procedure, a single chest tube was left in the pneumonectomy cavity and connected to a dedicated pneumonectomy drainage cassette. The chest tube was maintained for only 24 hours before removal, according to the postoperative clinical and radiological assessment.
This standardized five-step robotic approach provides a reproducible strategy for left pneumonectomy and may be particularly valuable after neoadjuvant chemoimmunotherapy, where precise dissection is required to safely manage treatment-related inflammatory and fibrotic hilar changes.
References
- Asban A, Pachos N, Snyder CA, et al. Largest single-institution series of robotic pneumonectomy. Front Surg. 2026;13:1841553. doi:10.3389/fsurg.2026.1841553.
- Soukiasian HJ, Brownlee AR. Robotic-assisted left pneumonectomy. JTCVS Tech. 2024;25:186-189. doi:10.1016/j.xjtc.2024.02.018.
- Srivatsa S, Maréchal H, Altorki NK, et al. Multicenter study comparing outcomes of robotic versus video-assisted thoracoscopic resection of non-small cell lung cancer following neoadjuvant chemoimmunotherapy. J Robot Surg. 2026;20:398. doi:10.1007/s11701-026-03326-4.
- Mordojovich G, Hugen N, Bottet B, Montagne F, Bouabdallah I, Pagès PB, Sarsam M, Thomas PA, Baste JM. New standardized five-zone lobectomy with structured assessment in robotic surgery: the French lobectomy. J Thorac Dis. 2025;17(4):2718-2729. doi:10.21037/jtd-24-1755
Disclaimer
The information and views presented on CTSNet.org represent the views of the authors and contributors of the material and not of CTSNet. Please review our full disclaimer page here.
 4 views on Vimeo